

 Nov 20, 2026
A portable nebulizer is a small device with an unusually demanding power requirement. The mesh or ultrasonic element has to vibrate at a stable frequency, the pump or driver has to hold output for the full dose, and the whole assembly has to survive being wiped down between patients. Unlike a consumer atomizer, where the worst case is a weak puff, a nebulizer that loses output mid-treatment delivers an incomplete dose, and that is a clinical event rather than a user annoyance.
This guide covers the battery side of that problem: which lithium chemistries suit atomizing devices, how capacity, continuous discharge rating and voltage interact, how the 18650 and 21700 formats compare with a flat pouch pack, and which medical requirements change the design compared with a consumer device. UFOPOWER is a professional lithium battery manufacturer supplying rechargeable cells and custom packs for medical, portable and atomizing equipment.

Atomization in medical use is not one load. A jet nebulizer drives a compressor and normally runs from mains power. An ultrasonic nebulizer vibrates a ceramic disc and draws a few watts. A mesh nebulizer drives a perforated membrane at high frequency and draws less, but needs a very stable supply because output depends on vibration amplitude. The battery has to match the profile, not just the average wattage.
| Nebulizer type | Typical electrical load | Battery relevance | Usual power source |
|---|---|---|---|
| Jet (compressor) nebulizer | 30 to 50 W, mains driven | Low, battery only for backup or transport units | Mains, sometimes with an internal backup pack |
| Ultrasonic nebulizer | 2 to 5 W during nebulization | High, the pack sets how many sessions per charge | 1S or 2S lithium, sometimes AA cells |
| Mesh nebulizer | 1 to 2 W, pulsed drive | High, and supply stability affects output | 1S lithium pouch or a small cylindrical cell |
Most high-performance atomizers use lithium-ion cells with a manganese or manganese-nickel blend in the cathode, commonly labelled IMR or INR. Compared with older lithium cobalt oxide cells, these chemistries are more tolerant of heat and of high discharge currents, which is why they became the default in devices that heat an element quickly. They also have lower internal resistance, so the voltage holds up better under a pulsed load.
For a medical nebulizer the reasoning is slightly different. The current is modest, so the cell is not stressed thermally by design. What matters is consistency over hundreds of sessions, predictable behaviour at end of life, and a supply chain that does not change the cell without notice. A manganese-blend cell with a well-characterised cycle life is a reasonable choice; a cheaper cobalt cell with a steeper ageing curve is not, even if the datasheet capacity looks better.
Lithium iron phosphate is the other credible option. It is more thermally stable and delivers 2,000 to 3,000 cycles, but it is heavier and has a lower nominal voltage, which complicates a 1S design that expects 3.7 V. In a handheld nebulizer where weight and size dominate, the manganese or NMC blend usually wins; in a transport ventilator or a larger clinic device, LiFePO4 becomes attractive.
Three numbers decide whether a cell is suitable, and they are frequently confused in marketing copy.
| Metric | What it means | Why it matters in a nebulizer |
|---|---|---|
| Capacity in mAh | Charge stored, so runtime at a given current | Sets the number of treatment sessions between charges |
| Continuous discharge rating, CDR | Current the cell can deliver continuously without overheating | A safety limit under fault or stall, not a performance target |
| Nominal voltage | Average voltage during discharge, 3.7 V for most lithium cells | Determines driver design and when output starts to fall |
The relationship between the three is Ohm's law at the load. Current equals voltage divided by resistance. A fully charged cell at 4.2 V driving a 0.2 ohm coil draws about 21 A, which is why high-drain atomizers need a cell rated at 25 A or more to keep a safety margin. That calculation belongs to the consumer and industrial side of atomization, where the load is a heating coil.
A medical mesh nebulizer is a different load. At 1.5 W and 3.7 V the current is about 0.41 A, roughly 0.2C on a 2,000 mAh cell. The CDR is not the binding constraint; voltage stability, temperature rise in a sealed handheld housing and cycle life are. Copying a high-drain consumer cell into a nebulizer adds cost and mass without improving the treatment, and it can make the pack larger than the enclosure allows.
Nebulizer users think in treatments, not in milliamp hours. A mesh nebulizer running 1.5 W for a ten-minute session uses about 0.25 Wh. A 1S 2,000 mAh pack holds 7.4 Wh, and at 80 percent usable capacity that is roughly 23 sessions. An ultrasonic unit at 3 W uses about 0.5 Wh per ten-minute session, so the same pack covers around 11 sessions. Both figures assume a healthy pack at room temperature; cold medication and a cold device reduce them.
| Pack | Energy | Mesh at 1.5 W | Ultrasonic at 3 W |
|---|---|---|---|
| 1S pouch, 2,000 mAh | 7.4 Wh | About 23 ten-minute sessions | About 11 sessions |
| 18650, 3,000 mAh | 11.1 Wh | About 35 sessions | About 17 sessions |
| 21700, 5,000 mAh | 18.5 Wh | About 59 sessions | About 29 sessions |
The cycle-life consequence is easy to miss. At three sessions a day a 500-cycle cell would take years to exhaust, so calendar ageing, not cycling, decides when the pack is replaced. That argues for a dated replacement interval in the service manual and a state-of-health estimate in the firmware, rather than waiting for a runtime complaint.
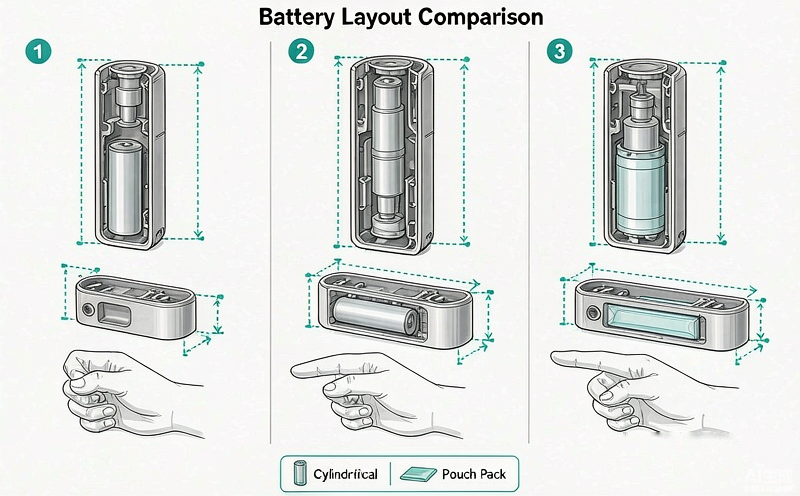
The atomizer industry standardised on two cylindrical formats, and both appear in medical devices, but the flat pouch is what makes a wearable or pocket nebulizer possible.
| Factor | 18650 | 21700 | Pouch (1S) |
|---|---|---|---|
| Typical capacity | 2,500 to 3,500 mAh | 4,000 to 5,000 mAh | 500 to 3,000 mAh, sized to the cavity |
| Mechanical protection | Rigid can, standard holder | Rigid can, larger holder | Depends on enclosure and compression |
| Space efficiency in a handheld | Moderate, round cell wastes corners | Lower, the device gets wider | Highest, follows the housing contour |
| Service model | User-replaceable, widely available | Replaceable, less common in retail | Sealed pack, factory or service replacement |
| Best fit | Clinic-grade handheld with a battery door | High-output transport or multi-patient units | Pocket and wearable nebulizers, sealed hygiene design |
The 21700 wins when capacity per device matters and the enclosure can grow, which is why it appears in high-output units. The 18650 remains the pragmatic choice where the user must be able to swap a cell. The pouch is the only option when the device has to be thin, sealed and cleanable, and it is the format most medical OEMs end up choosing for a pocket nebulizer.
The basic rules for atomizer cells transfer directly to medical devices, with extra weight on inspection because the device is handled by staff rather than an enthusiast.
• Inspect the wrap. The plastic sleeve is the only insulation on a cylindrical cell; a torn wrap can short against the metal housing. Never return a damaged cell to service.
• Use the specified charger. USB charging inside the device is convenient, but a dedicated charger gives a more balanced and controlled charge, and it keeps charging away from the patient.
• Stay inside the current limit. Check the load before firing a new or repaired assembly, and verify the stall current, not just the running current.
• Store and carry correctly. Loose cells in a pocket or a drawer with metal objects are a short-circuit waiting to happen; use a case or leave them in the device.
• Control the charging environment. A charging cabinet shared by a ward should hold packs at ambient temperature, not next to a radiator or in direct sun.
Four requirements separate a medical nebulizer pack from a consumer atomizer pack, and each one has a battery consequence.
Dose delivery. Nebulizing systems are assessed under ISO 27427, which sets out performance requirements including output rate and delivered dose. If the battery voltage falls and the mesh amplitude drops, the output rate changes and the delivered dose changes with it. The firmware must therefore regulate the drive, and the low-battery threshold must be set so that output stays within specification until the device annunciates and stops.
Patient-connected equipment. Under IEC 60601-1, charging while the patient is connected needs justification. Most designs inhibit nebulization during charge, or isolate the charging input, and the rationale belongs in the risk file rather than in a marketing note. For home-use devices, IEC 60601-1-11 adds requirements around the domestic environment, including misuse and cable handling.
Cleaning and contamination. The medication path and the battery compartment must be separated, because cleaning agents and spilled drug solution are both hostile to a pack. The compartment needs a gasket, a drain or vent path, and a connector that does not sit at the lowest point where liquid collects.
Battery evidence. The pack needs IEC 62133-2 reports and a UN 38.3 transport summary. NiMH alternatives fall under IEC 61951-2. None of these replace the device-level assessment, and a supplier who presents them as a 60601 certificate is misstating scope.
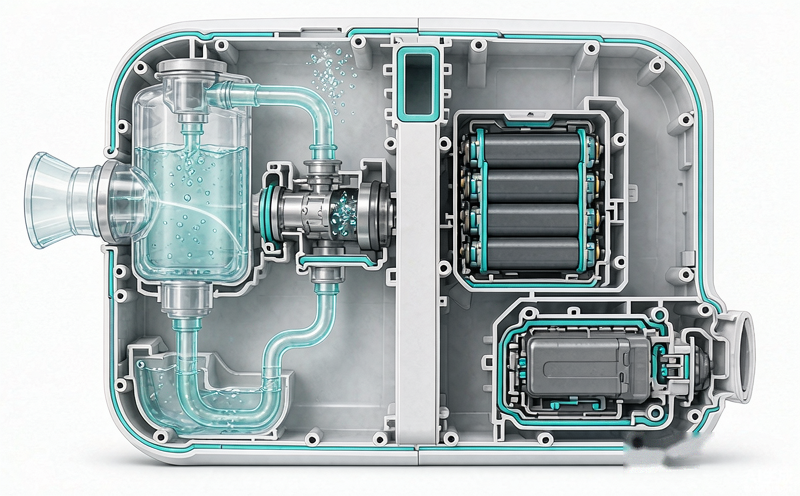
A nebulizer pack specification that is written properly answers six questions: what the drive stage draws in normal and stall conditions, how many sessions per charge the user expects, what the device does when the pack is nearly empty, how the pack is charged and by whom, what it has to survive in cleaning, and how the pack is identified and replaced. Everything else follows from those answers.
• Nominal voltage and the minimum voltage at which the drive still meets its output specification
• Continuous and peak current of the drive, with the stall case included
• Sessions per charge at the stated session length and medication volume
• Protection thresholds, temperature sensing and charge inhibit behaviour
• Cleaning agents, ingress level and the drop profile the pack must survive
• Serial traceability, replacement interval and end-of-life handling
For OEM programmes, UFOPOWER builds both routes: replaceable cylindrical cells for devices with a battery door, and sealed custom pouch packs with protection board, NTC and a keyed connector for pocket nebulizers. As a professional lithium battery manufacturer with in-house production and factory-direct OEM/ODM support, the team sizes the pack from the session profile rather than from a capacity guess, and supplies IEC 62133-2 reports and UN 38.3 test summaries for the device file.
Solid-state cells remove the liquid electrolyte, which promises better tolerance of abuse and faster charging, and both would be welcome in a handheld medical device. The technology is moving quickly, but for a device programme starting now it is a development risk rather than a design input: cost is higher, low-temperature behaviour and cycle data are still thin, and the supply base is limited. The sensible position is to design the current pack so that a future cell with a similar footprint and a higher safe voltage window could be qualified later, without committing the launch schedule to it.
The consumer atomizer world optimises for heat-up speed and cloud size, which pushes designers toward high-drain cells and low-resistance loads. A medical nebulizer optimises for delivered dose, hygiene and predictable service life, which pushes the design in a different direction: a modest-current cell with a stable discharge curve, a drive stage that holds output as the pack drains, and a sealed pack that survives cleaning.
Get those three right and the format question becomes simple. If the user must swap cells, use a standardised cylindrical cell and give them a proper charger. If the device has to be pocket-sized and sealed, use a custom pouch pack and manage the replacement interval through the service channel. Either way, the number that matters is sessions per charge at the specified output, not the capacity printed on the label.
Which battery chemistry is best for a portable nebulizer?
Do nebulizers need a high-discharge cell?
18650 or 21700 for a medical nebulizer?
How many treatments can a nebulizer battery deliver per charge?
Why does battery voltage matter for dose delivery?
Can a nebulizer be used while charging?
What battery documents should a nebulizer OEM request?



Nebulizer Battery Guide: 18650 vs 21700 and CDR

Medical Scale Batteries: Rechargeable vs Disposable


 WhatsApp
 EN
 AR
 DE
 ES
 FR
 JP
 KO
 PT
 RU
 Home >











